Dr. Isha Agarwalla is one of the very few FAICO-fellowship-trained oculoplastic and lacrimal surgeons available in Uttarakhand. Her FAICO fellowship specifically covered lacrimal surgery — including DCR, canalicular repair, lacrimal intubation, and complex reconstruction. She manages the full spectrum of watery eye conditions at Raahi Netradham, from dry eye and allergy through to DCR surgery for blocked tear ducts in adults and children.

Book Appointment
Schedule Your Visit
Fill out the appointment form and our team will contact you shortly.
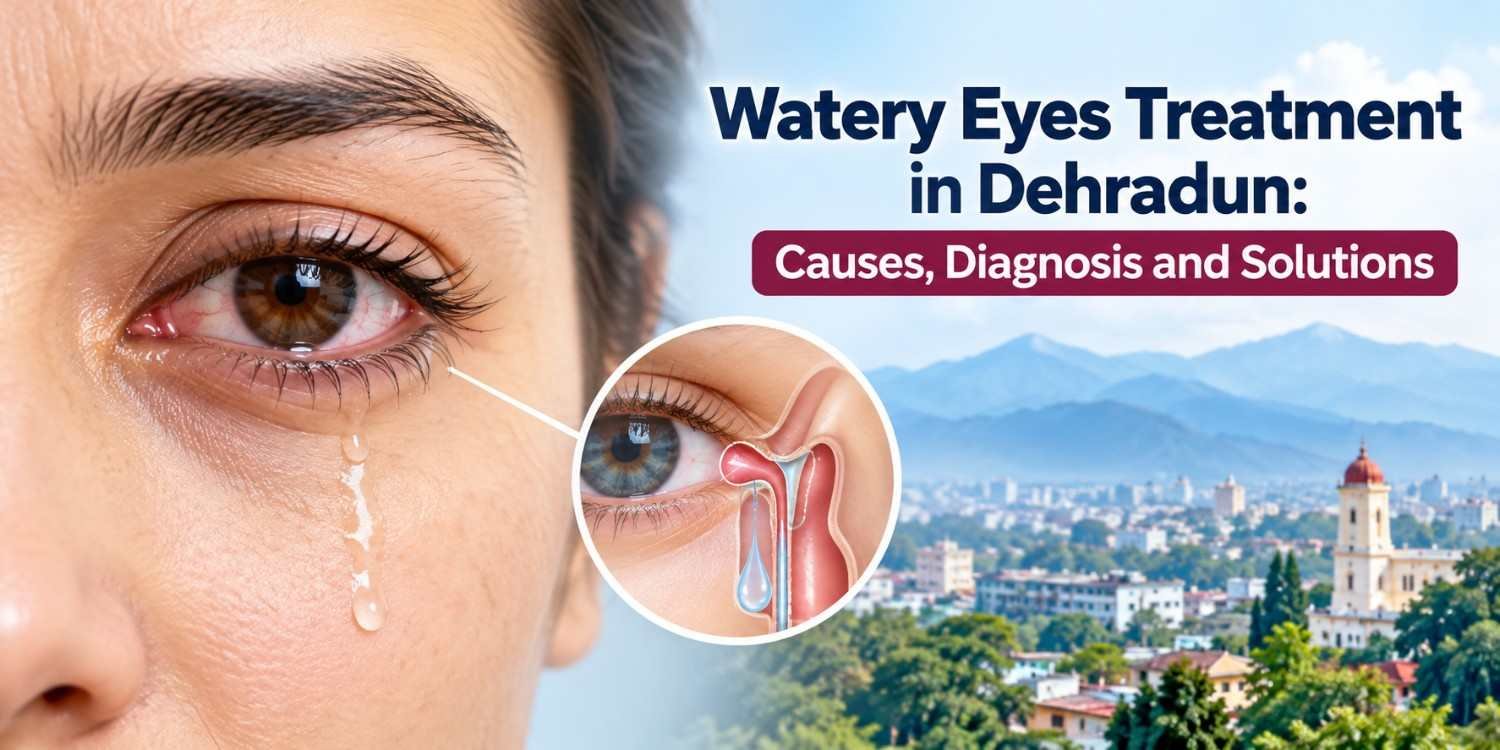
Watery Eyes Treatment in Dehradun: Causes, Diagnosis and Solutions
Tears down the cheek when you have not been crying. One eye that waters in the wind, in sunlight, reading, cooking, or apparently at random — every day. Tissue in your pocket because your eye just never stops. For many patients across Dehradun, Haridwar, and the surrounding Uttarakhand region, this is not a minor inconvenience. It is a constant, embarrassing, occasionally painful daily companion that has been incorrectly managed with antibiotic drops for months or years.
Persistent watery eye — medically called epiphora — is one of the most under-referred conditions in general ophthalmology. Patients are given drops that help briefly and then come back. The fundamental cause — often a blocked tear drainage channel — is never addressed. And the watering never permanently stops.
This guide explains why eyes water persistently, what the different causes mean, how to tell which cause is most likely, and what the correct treatment is for each — including when drops genuinely help and when surgery is the only solution that works. For patients in Dehradun and across Uttarakhand, Dr. Isha Agarwalla at Raahi Netradham provides the full range of watery eye treatment — from medical management through to DCR surgery — in one clinic, without referral to Delhi.
Persistent Watery Eye? Book an Evaluation at Raahi Netradham
Dr. Isha Agarwalla — FAICO Oculoplasty & Lacrimal Specialist | NABH Accredited | Dehradun
Book Your Eye Consultation in Dehradun
Get comprehensive eye care at Raahi Netradham with fellowship specialists, advanced diagnostics, and in-house treatment facilities.
What This Guide Covers
- • How the tear drainage system works — the anatomy behind watery eyes
- • The most important distinction: drainage problem vs production problem
- • Cause 1 — Blocked tear duct (nasolacrimal duct obstruction)
- • Cause 2 — Dry eye disease (paradoxical reflex tearing)
- • Cause 3 — Eyelid malposition (entropion / ectropion)
- • Cause 4 — Allergy and seasonal conjunctivitis
- • Cause 5 — Infection and dacryocystitis
- • Cause 6 — Surface irritation and foreign body
- • Cause 7 — Punctal stenosis
- • The diagnosis — how Dr. Isha identifies the correct cause
- • Treatment — matched to cause
- • DCR surgery — the definitive solution for blocked tear ducts
- • Watery eyes in babies and infants
- • FAQs — answered directly
How the Tear Drainage System Works
Understanding why eyes water persistently requires a basic understanding of how tears are normally managed — because watery eye is almost always a problem with drainage, not just with tear production.
Tears are produced continuously by the lacrimal gland above the outer corner of each eye, supplemented by accessory glands throughout the conjunctiva. They spread across the eye surface with each blink, keeping the cornea moist and clear. At the inner corner of each eye — the medial canthus — two tiny openings called puncta (upper and lower) drain tears from the eye surface into small canals called canaliculi. These canaliculi join to form the lacrimal sac, which connects downward through the nasolacrimal duct — running through the bone between the eye and the nose — into the inferior nasal meatus, where tears are eventually absorbed or evaporated.
When this drainage pathway is working correctly, tears drain away continuously and the eye stays moist without overflowing. When any part of this pathway is blocked, narrowed, or misdirected, tears cannot drain — and they overflow down the cheek. This is epiphora.
The Plumbing Analogy
Think of the tear drainage system as a sink. The lacrimal gland produces water (tears) continuously. The puncta are the plughole. The canaliculi and nasolacrimal duct are the pipe. If the pipe is blocked — at any point from the punctum to the nasal meatus — the sink overflows. Putting drops in the eye is like adding detergent to an overflowing sink — it treats the surface but does nothing to unblock the pipe.
The Most Important Distinction — Drainage Problem vs Production Problem
Not all watery eyes have the same cause. Correctly identifying whether the problem is in the drainage system (structural) or in tear production (excessive reflex tearing) determines the correct treatment entirely.
| Category | Mechanism | Key Clue | Treatment Direction |
|---|---|---|---|
| Drainage problem | Tear duct blocked or narrow — tears cannot drain | Usually ONE eye, constant, no clear trigger | Structural — lacrimal surgery (DCR, probing, dilation) |
| Reflex overproduction | Eye produces excessive tears in response to irritation | Often BOTH eyes, triggered by wind/light/dryness | Treat the underlying irritant — dry eye, allergy, infection |
| Eyelid misdirection | Lid or punctum turned inward/outward — tears overflow | Visible eyelid abnormality on examination | Surgical correction of lid position |
| Mixed cause | Some drainage + some reflex component | Both eyes affected but worse on one side | Address both components — assessment needed |
This distinction cannot be made reliably from symptoms alone. A specialist examination — using slit lamp, lacrimal syringing, and clinical tests — is needed to identify which of these mechanisms is driving the watering in each individual patient.
Cause 1 — Blocked Tear Duct (Nasolacrimal Duct Obstruction)
Nasolacrimal duct obstruction (NLDO) is the most common structural cause of persistent watery eye in adults — and the one most frequently undertreated with antibiotic drops instead of referred for definitive surgical management.
What causes nasolacrimal duct obstruction?
- Age-related changes in the duct lining — the most common cause in adults over 50
- Chronic sinusitis or nasal polyps — inflammatory changes affecting the duct from the nasal side
- Previous nasal or facial trauma — structural disruption of the bony channel
- Post-radiotherapy changes — radiation for nasal or sinus tumours
- Certain medications — some topical eye drops can cause secondary duct stenosis
- Dacryoliths — calcium deposits forming a stone-like obstruction within the lacrimal sac
- Idiopathic — many cases develop without a clearly identifiable cause
What it feels like
- Constant or frequent watering from one eye — tears overflow down the cheek
- Mucoid or mucopurulent discharge from the inner corner of the eye — particularly in the morning
- Recurrent swelling or infection near the inner corner of the eye (dacryocystitis)
- Pressing over the lacrimal sac area may produce a reflux of mucus or pus through the punctum
- Symptoms worse in cold, windy conditions or when outdoors — because wind increases tear production beyond the drainage capacity
🔴 The Dacryocystitis Warning
If you notice a tender, swollen lump at the inner corner of your eye — between your eye and your nose — this is dacryocystitis: an acute infection of the blocked lacrimal sac. It requires urgent treatment with antibiotics and, once the acute infection settles, definitive DCR surgery to prevent recurrence. Do not ignore a painful swelling at the inner corner of the eye.
Why eye drops do not cure it
Antibiotic drops treat secondary bacterial overgrowth in the stagnant tear pool sitting behind the obstruction. They reduce discharge and infection — temporarily. The moment the drops are stopped, the stagnant pool becomes infected again and symptoms return. The obstruction itself — the blocked duct — is a structural problem that cannot be dissolved or medicated away. DCR surgery is the only definitive treatment.
Cause 2 — Dry Eye Disease (Paradoxical Reflex Tearing)
Dry eye as a cause of watery eyes seems counterintuitive — but it is one of the most common causes of bilateral persistent watering, particularly in Dehradun's dry winter climate and increasingly prevalent in the city's screen-heavy professional population.
How dry eye causes watery eyes
When the eye surface is dry or irritated, the cornea sends a signal to the reflex lacrimal gland — which responds by producing a large bolus of watery tears. These reflex tears flood the drainage system, overwhelm its capacity, and overflow down the cheek. The patient feels like they are crying. The irony is that they are — but from dryness, not sadness.
These reflex tears are watery and profuse but do not lubricate the eye effectively — they wash away rapidly without replacing the stable tear film. The eye remains dry between episodes, and the cycle continues.
How to tell if dry eye is causing your watering
- Both eyes affected — not just one
- Worse on screens, in air conditioning, or in the Dehradun winter wind
- Burning, stinging, or grittiness between watering episodes
- Watering particularly noticeable in bright light or outdoors
- Screen use makes it worse — less blinking on computers dries the surface faster
- Significantly improves temporarily with lubricating drops
Treatment
Preservative-free lubricating drops, lid hygiene, warm compresses, reduced screen time with regular blinking breaks, and — where the tear film is significantly unstable — anti-inflammatory drops (cyclosporine or lifitegrast). In moderate-severe cases, punctal plugs can reduce tear drainage to preserve existing tears. Dry eye causing watery eyes responds very well to correct treatment — but requires consistent management rather than occasional drops.
Cause 3 — Eyelid Malposition (Entropion / Ectropion)
Entropion — inward-turning eyelid
When the lower eyelid turns inward, the eyelashes rub against the corneal surface. This causes intense irritation, reflex tearing, redness, and foreign body sensation. If untreated, lash rubbing can cause corneal abrasion and scarring. Entropion is most common in older adults and is corrected with minor outpatient surgery by Dr. Isha Agarwalla.
Ectropion — outward-turning eyelid
When the lower eyelid turns outward — away from the eye — the punctum (tear drainage opening) is no longer in contact with the eye surface. Tears cannot enter the drainage canal and overflow down the cheek instead. Ectropion also exposes the inner conjunctival surface, causing chronic irritation and further tearing. Surgical correction restores normal lid position and resolves the watering.
Punctal eversion
Even without full ectropion, the punctum can be slightly everted (turned outward) — a subtle finding on examination that prevents efficient tear drainage. This is addressed with minor surgical punctal procedures.
Cause 4 — Allergy and Seasonal Conjunctivitis
Allergic conjunctivitis is extremely common in Dehradun — particularly during the spring and early monsoon seasons when pollen counts and airborne allergens are highest. The eye responds to allergen exposure with mast cell activation, histamine release, and intense reflex tearing alongside itching, redness, and swelling.
Key features of allergic watering
- Both eyes affected simultaneously
- Itching — the defining symptom that distinguishes allergy from blocked duct
- Seasonal pattern — worse in spring (March-May) and post-monsoon in Dehradun
- History of hay fever, asthma, or skin allergy
- Immediate improvement with antihistamine drops
- Mucoid (stringy) rather than watery discharge in some patients
Treatment
Topical antihistamine/mast cell stabiliser drops (olopatadine, ketotifen), allergen avoidance where feasible, cool compresses, and preservative-free lubricants to wash allergens from the eye surface. Severe seasonal cases may benefit from topical steroid drops under specialist supervision. Desensitisation (immunotherapy) is an option for recalcitrant cases managed in collaboration with an allergist.
Cause 5 — Infection and Dacryocystitis
Acute bacterial conjunctivitis
Bacterial conjunctivitis produces a mucopurulent (mucus plus pus) discharge rather than purely watery overflow. The discharge is typically thicker, more yellowish-green, and causes the eyelids to stick together in the morning. It usually affects both eyes (though may start in one), is highly contagious, and responds well to antibiotic drops — unlike blocked duct watering which does not.
Chronic dacryocystitis
When a blocked tear duct becomes chronically infected, the lacrimal sac contains stagnant, infected fluid. The patient notices persistent discharge from the inner corner, recurrent swelling, and occasional acute flare-ups of painful dacryocystitis. Chronic dacryocystitis is managed with antibiotic treatment for acute episodes followed by definitive DCR surgery to eliminate the chronically infected sac and restore drainage.
Viral conjunctivitis
Adenoviral conjunctivitis (the most common viral cause) produces profuse watery discharge — not purulent — with intense redness, light sensitivity, and sometimes a pre-auricular lymph node swelling. It is highly contagious, lasts 2-3 weeks, and does not respond to antibiotics. Management is supportive — cold compresses, lubricating drops, hygiene to prevent spread.
Cause 6 — Surface Irritation and Foreign Body
The cornea is one of the most densely innervated surfaces in the human body. Any irritation to its surface — a dust particle, a loose eyelash, a contact lens deposit, a corneal abrasion, or early keratitis — triggers intense reflex tearing as the eye attempts to flush the irritant away.
- Foreign body in the eye — a common cause of sudden-onset acute watering
- Loose eyelashes (trichiasis) — lashes growing inward, brushing the corneal surface at each blink
- Contact lens intolerance — overwear, deposit buildup, or poor fit
- Corneal abrasion — scratch from a twig, fingernail, or contact lens
- Corneal infections (keratitis) — can cause intense watering with pain and light sensitivity
Sudden Watering With Pain and Light Sensitivity
If watery eye is accompanied by significant pain, intense light sensitivity (photophobia), and blurred vision — this may indicate corneal disease (ulcer, keratitis) or acute uveitis. These are urgent conditions — call Raahi Netradham immediately or attend the clinic on the same day. Do not delay with home remedies.
Cause 7 — Punctal Stenosis
The puncta — the tiny drainage openings at the inner corner of each eyelid — can narrow or close (stenose) due to chronic inflammation, prolonged use of certain eye drops (particularly those containing preservatives), age-related changes, or previous infection. When the puncta are too small to accept the normal flow of tears, drainage is impaired and the eye waters.
Punctal stenosis is identified on slit lamp examination and treated with punctal dilation (a brief, painless in-clinic procedure using a dilator to widen the punctal opening) or, in more severe cases, a small surgical procedure called a three-snip punctoplasty.
Not Sure Why Your Eye Is Watering? Book an Evaluation
Dr. Isha Agarwalla identifies the correct cause and recommends the right treatment — not more drops
📞 Call +91 7078082666 | 💬 WhatsApp | 🌐 raahinetradham.com
Diagnosis at Raahi Netradham — Finding the Right Cause
Watery eye cannot be correctly managed without identifying the specific cause. At Raahi Netradham, Dr. Isha Agarwalla performs a structured lacrimal and oculoplastic evaluation that includes:
- Full history — which eye(s), how long, any discharge, any swelling, any trigger factors, any previous treatment
- Slit lamp examination — corneal surface, eyelid margins, punctal position and patency, conjunctival health
- Punctal examination — size, position, and whether the punctum is everted, stenosed, or atretic
- Lacrimal syringing and irrigation — saline is gently flushed through the lacrimal drainage system using a fine cannula. If the saline passes into the nose, the system is patent. If it refluxes back out of the eye, the duct is blocked. The level of obstruction can often be determined from the irrigation pattern
- Probing — a fine probe is passed through the canaliculus to assess the lacrimal anatomy
- Dacryocystography or CT dacryocystogram — imaging of the drainage system where complex anatomy or previous trauma makes syringing findings uncertain
- Eyelid assessment — lid position, laxity, and margin examination
After this assessment, Dr. Isha explains the diagnosis clearly — where the obstruction or dysfunction is, what it means, and what treatment is recommended. Patients are never left uncertain about why their eye is watering or what comes next.
Treatment — Matched to Cause
| Cause | Is This Curable? | Treatment | Does Surgery Help? |
|---|---|---|---|
| Blocked nasolacrimal duct (NLDO) | Yes — permanently | DCR surgery | ✅ Yes — definitive cure in 90%+ |
| Dry eye reflex tearing | Yes — manageable | Preservative-free drops, lid hygiene, anti-inflammatory drops | Usually no surgery — medical treatment |
| Entropion (inward eyelid) | Yes — surgically | Minor lid surgery | ✅ Yes — quick, effective |
| Ectropion (outward eyelid) | Yes — surgically | Minor lid surgery to restore punctum position | ✅ Yes |
| Punctal stenosis | Yes | Dilation or three-snip punctoplasty | ✅ Yes — minor in-clinic procedure |
| Allergic conjunctivitis | Controlled — not cured | Antihistamine/mast cell stabiliser drops | Usually no — medical treatment |
| Bacterial conjunctivitis | Yes — self-limiting | Antibiotic drops for 7-10 days | No — antibiotic drops sufficient |
| Viral conjunctivitis | Self-resolving | Supportive care — lubricants, cold compresses | No — self-limiting |
| Foreign body / surface irritation | Yes — remove the irritant | Foreign body removal; treat corneal disease | Only if corneal damage requires treatment |
| Canalicular obstruction | Partial | Canalicular intubation or CDCR surgery | ✅ Yes — specialist lacrimal surgery |
DCR Surgery — The Definitive Solution for Blocked Tear Ducts
Dacryocystorhinostomy (DCR) is the gold-standard treatment for nasolacrimal duct obstruction. It creates a new opening directly from the lacrimal sac into the nasal cavity — bypassing the blocked duct entirely — and allows tears to drain normally.
Two approaches to DCR
| Approach | How It Is Done | Scar | When Preferred |
|---|---|---|---|
| External DCR | A small incision (approximately 1.5cm) at the side of the nose, lateral to the inner canthus. The lacrimal sac is opened and a new opening created into the nasal mucosa. | Small external scar — fades significantly over 3-6 months | Most cases — higher long-term success rate, slightly better view of anatomy |
| Endoscopic (endonasal) DCR | Performed entirely through the nose using a rigid nasal endoscope — no external incision. | No visible scar | Patients strongly concerned about scarring; revision cases where external approach may be more complex |
What happens during DCR
- Local or general anaesthesia is administered — most adult DCR procedures are performed under local anaesthesia with sedation
- An opening is created in the nasolacrimal fossa bone — the thin bone separating the lacrimal sac from the nasal cavity
- The lacrimal sac mucosa and nasal mucosa are opened and sutured together to create a permanent new drainage opening
- A fine silicone intubation tube (Crawford tube or O'Donoghue tube) is threaded through the system and left in place to keep the new opening patent while healing occurs
- The skin incision is closed with absorbable sutures
After DCR surgery
- Most patients are discharged the same day
- Bruising and swelling around the eye and nose is normal and typically settles within 7-10 days
- Antibiotic drops and nasal decongestant spray are prescribed for the healing period
- The silicone tube is removed in clinic after 3 to 6 months — a quick, painless procedure
- Most patients notice the watering has reduced or resolved within the first few weeks after surgery
- Final success is assessed at the 3-6 month follow-up once the tube has been removed
Success rate
DCR surgery performed by an experienced lacrimal surgeon has a success rate of over 90% for primary nasolacrimal duct obstruction. Revision cases (where a previous DCR has failed) have a slightly lower success rate and may require a different approach. At Raahi Netradham, Dr. Isha Agarwalla performs both external and endoscopic DCR.
💬 Real Patient Story — Dehradun
"3 saal se ek aankhon se paani aata tha. Har clinic mein antibiotic drops mili — aur drops band karne ke 2-3 din baad wapas shuru. Dr. Isha ne pehli baar properly check kiya — syringing kiya, bola duct band hai, DCR karna padega. Operation hua, 10 din mein swelling gayi. 6 mahine ho gaye hain — aankhon se paani aana band. Pehle itna simple solution kyun nahi bataya kisi ne?"
— Meena Bisht, 58, Clement Town, Dehradun ("For 3 years one eye was watering. Every clinic gave antibiotic drops — and 2-3 days after stopping, it started again. Dr. Isha examined me properly for the first time — did syringing, said the duct is blocked, DCR is needed. Surgery done, swelling gone in 10 days. It has been 6 months — the watering has stopped. Why did nobody tell me such a simple solution before?")
Watery Eyes in Babies and Infants
Congenital nasolacrimal duct obstruction (CNLDO) is common — affecting approximately 6-20% of newborns. The nasolacrimal duct fails to fully open at birth, causing one or both eyes to water constantly with recurrent sticky discharge from the first weeks of life.
Management in infants
- Lacrimal massage (Crigler massage) — parents are taught to massage gently over the nasolacrimal sac area, increasing hydrostatic pressure that can help open the duct. Effective in many infants when started early
- Antibiotic drops — for managing secondary infection; do not cure the obstruction
- Probing and irrigation — a brief procedure under general anaesthesia where a fine probe is passed through the duct to open the blockage. Usually recommended between ages 9-18 months if massage has not resolved the obstruction
- Silicone intubation — if probing does not succeed, a silicone tube is placed through the duct
- DCR surgery — rarely needed in infants but considered in complex or failed cases
Most cases of congenital watery eye resolve spontaneously by age 12-18 months. If your infant's eye has been watering since birth with discharge, early evaluation at Raahi Netradham allows Dr. Isha to guide the appropriate management for the child's age and clinical picture.
Watery Eye Treatment at Raahi Netradham — Dr. Isha Agarwalla
Dr. Isha Agarwalla | MBBS | DNB | FAICO | MNAMS
Oculoplastic & Lacrimal Surgeon — Raahi Netradham Eye Clinic, Dehradun
Services Available at Raahi Netradham for Watery Eye:
Lacrimal syringing and probing · DCR surgery (external and endoscopic) · Punctal dilation and three-snip punctoplasty · Lacrimal intubation · Canalicular repair · Congenital watery eye management · Dry eye assessment and treatment · Lid margin evaluation and surgery (entropion/ectropion) · Botulinum toxin for reflex tearing in selected cases
💬 Dr. Isha Agarwalla — Oculoplasty & Lacrimal Specialist, Raahi Netradham
"The single most common clinical scenario I see with watery eyes is a patient who has been using antibiotic drops for years for what is actually a blocked tear duct. Drops cannot unblock a duct. The diagnosis requires syringing — a five-minute procedure in clinic — and the treatment requires surgery. Most patients who finally have the DCR tell me they wish they had done it years earlier."
Book a Consultation With Dr. Isha Agarwalla
Oculoplasty | Cataract | Ocular Oncology — Raahi Netradham, Dehradun | NABH Accredited
Frequently Asked Questions
Not necessarily — cold and wind increase tear production and can overwhelm an otherwise adequate drainage system, particularly in a duct that is partially narrow rather than fully blocked. However, if the watering is persistent indoors as well, or if there is discharge or recurrent infection, a blocked duct is more likely. An evaluation with lacrimal syringing at Raahi Netradham will clarify whether there is an obstruction.
This is the classic presentation of a blocked nasolacrimal duct with secondary infection. The antibiotics treat the infection in the stagnant tear pool — which is why symptoms improve temporarily — but as soon as the drops are stopped, the stagnant pool becomes infected again and discharge returns. You need lacrimal syringing to confirm the obstruction and a discussion with Dr. Isha about DCR surgery, which will resolve this permanently.
DCR is performed under local anaesthesia with sedation in most adults — you are comfortable and relaxed during the procedure. After surgery, there is swelling and bruising around the nose and eye for 7-10 days. Mild discomfort during this period is managed with standard pain relief. Most patients describe the recovery as much easier than they expected. The nose may feel slightly congested for a few weeks as the nasal mucosa heals.
The external DCR incision (approximately 1.5cm alongside the nose) heals very well in most patients. The scar is typically faint and positioned where it is not prominently visible in normal conversation. Most patients find the scar has faded significantly by 3-6 months. For patients with significant scar concerns, endoscopic DCR (no external incision) is available and discussed at consultation.
Yes — and this is one of the most common misunderstandings in eye care. Dry eye triggers reflex tearing — the eye surface is irritated by dryness and the reflex lacrimal gland produces a large burst of watery tears. These overflow down the cheek. The patient feels like they are crying. The eye is simultaneously dry (inadequate stable tear film) and wet (excessive reflex tears). The solution is treating the dry eye — not prescribing antibiotics, which are ineffective for this type of watering.
Congenital nasolacrimal duct obstruction is common and most cases resolve spontaneously by 12-18 months with lacrimal massage. However, it is worth having the child evaluated early so that the correct technique for lacrimal massage can be demonstrated, antibiotic drops can be prescribed for any discharge, and a plan for probing under anaesthesia can be made if the obstruction has not resolved by the appropriate age. Bring your infant to Raahi Netradham for an evaluation — Dr. Isha will guide the management appropriate for your child's age and clinical findings.
DCR surgery creates a permanent new drainage pathway. In the over 90% of cases where the surgery succeeds, the result is lasting — patients remain free of the watering indefinitely. The silicone tube placed during surgery is removed after 3-6 months; after removal, the new opening remains open because it is lined by mucosa from both the lacrimal sac and the nasal cavity. Occasional late failure can occur but is relatively uncommon; revision surgery is available if needed.