
Schedule Your Visit
Fill out the appointment form and our team will contact you shortly.
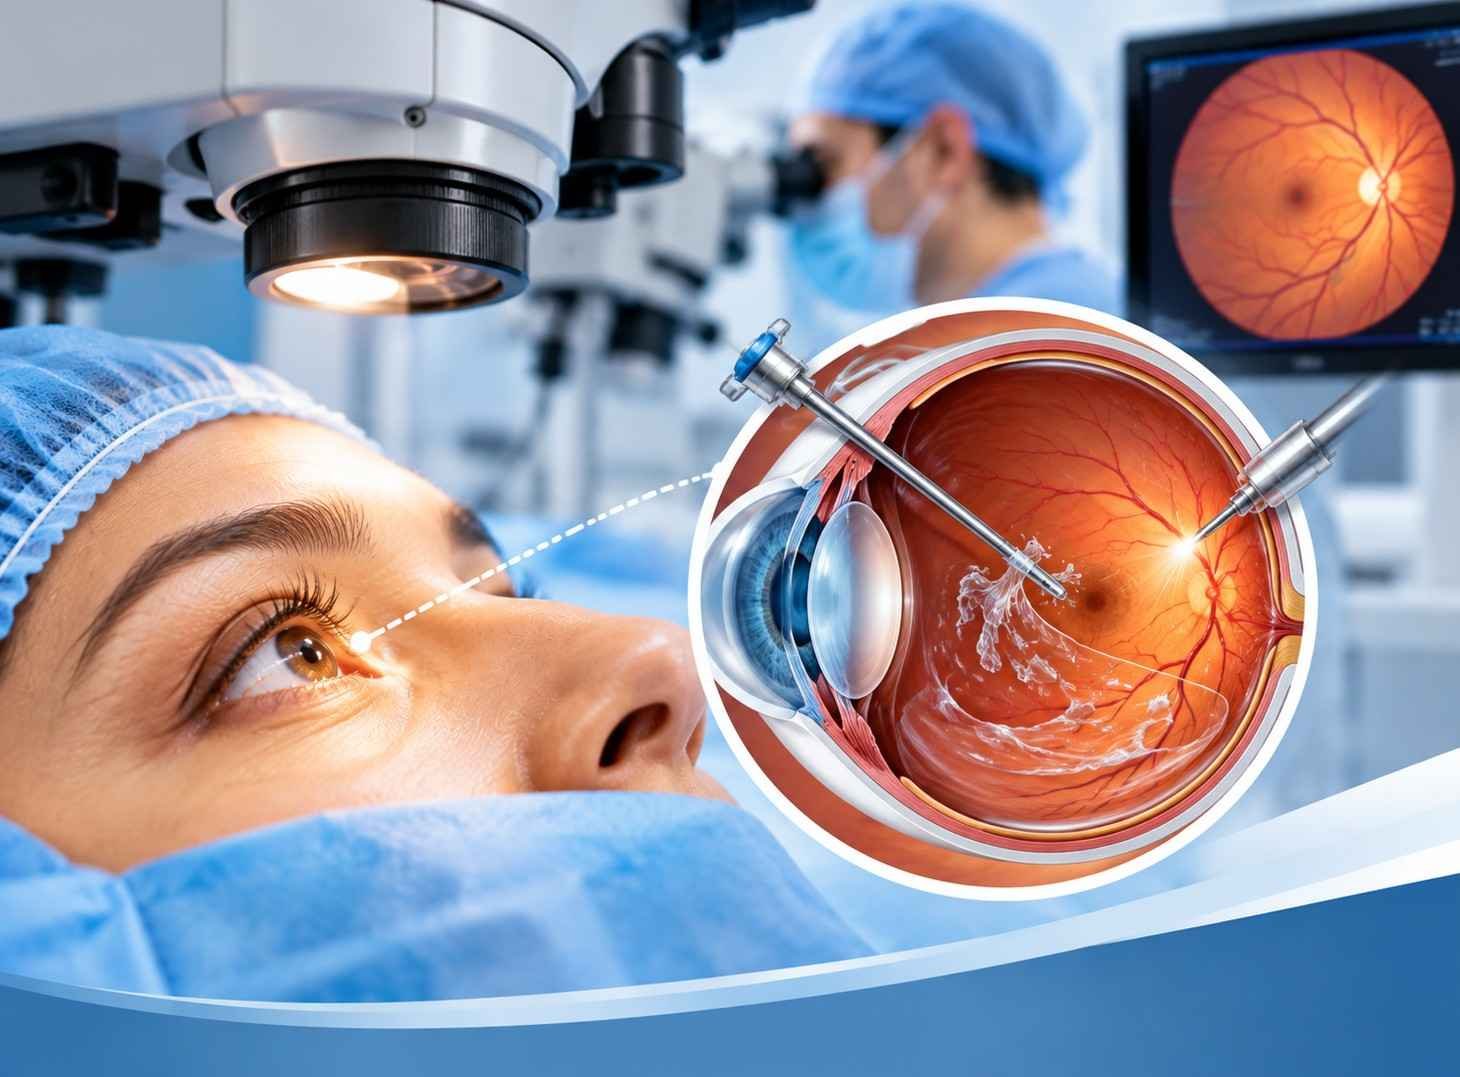
What Is Vitrectomy Surgery? When Do You Need It and What to Expect
When patients across Dehradun and Uttarakhand are told they need vitrectomy surgery, they often come with the same set of questions. What exactly is being done inside the eye? Will it hurt? How long does it take? Will I need to lie face-down? Will my vision improve — and how much? How long will recovery take? And most importantly: why is this surgery being recommended for my specific condition?
Vitrectomy is one of the most important procedures in modern ophthalmology — and one of the least understood by patients. It is referenced throughout blogs on retinal detachment, macular hole, diabetic retinopathy, and vitreous haemorrhage, but never explained in full as a procedure in its own right.
This guide changes that. It explains vitrectomy completely — the anatomy involved, the conditions that require it, exactly what happens during surgery step by step, what gas tamponade means and why face-down positioning is needed, the recovery timeline, the risks, and what to expect in the months after surgery. Written for patients in Dehradun, Uttarakhand, and across India who have been told they need vitrectomy and want to understand it before they arrive at the operating table.
Questions About Vitrectomy? Consult Dr. Mohit Garg at Raahi Netradham
Dr. Mohit Garg — FVRS Trained | 25G/27G In-House | NABH Accredited | Same-Day Emergency Surgery | Dehradun
Book Your Eye Consultation in Dehradun
Get comprehensive eye care at Raahi Netradham with fellowship specialists, advanced diagnostics, and in-house treatment facilities.
What We'll Cover
- • The vitreous — what it is and why it matters surgically
- • What vitrectomy surgery actually involves
- • The conditions that require vitrectomy — and why
- • 25G and 27G micro-incision vitrectomy — what it means for patients
- • The surgical steps — a plain-English walkthrough
- • Gas tamponade and silicone oil — what fills the eye after surgery
- • Face-down positioning — why it is needed and for how long
- • Combined phaco-vitrectomy — when cataract and vitrectomy are done together
- • Recovery — what to expect week by week
- • Risks of vitrectomy — honest information
- • Vitrectomy at Raahi Netradham, Dehradun
- • FAQs — answered directly
The Vitreous — What It Is and Why Removing It Allows Retinal Surgery
The vitreous is the clear, gel-like substance that fills the large chamber of the eye between the crystalline lens and the retina — occupying approximately 80% of the eye's volume. In a young eye, it is a firm, uniform gel. With age, it liquefies and eventually separates from the retinal surface (posterior vitreous detachment).
The vitreous is transparent and normally does not obstruct vision. However, it can become a problem when it bleeds (vitreous haemorrhage), when it pulls on the retina (vitreoretinal traction causing detachment or macular distortion), or when it contains infection or foreign material.
Most importantly, the vitreous physically prevents direct surgical access to the retina. To operate on the retina — to repair a detachment, peel a membrane, close a macular hole — the surgeon must first remove the vitreous. Vitrectomy (from 'vitreous' + Greek 'ektome' — excision) is that removal. Once the vitreous is cleared, the retina is directly accessible for any required surgical manipulation.
Why Vitrectomy Changed Retinal Surgery
Before vitrectomy was developed in the 1970s by Dr. Robert Machemer, surgeons had no reliable way to access and operate on the posterior retina. Retinal detachment was often managed with scleral buckling alone — a technique that supports the retina from outside the eye but cannot directly manipulate it. Modern vitrectomy transformed retinal surgery, making previously inoperable conditions routinely treatable and dramatically improving outcomes for the most complex retinal diseases.
Conditions That Require Vitrectomy Surgery
Vitrectomy is not a single-purpose procedure — it is the foundational surgical platform for a range of retinal and vitreoretinal conditions. Here is a complete guide to when it is needed and why:
| Condition | Why Vitrectomy Is Needed | Urgency |
|---|---|---|
| Retinal detachment (rhegmatogenous) | Remove vitreous traction; tamponade the retina with gas; seal breaks with laser — particularly for complex or posterior detachments | 🚨 Urgent — same day or next morning |
| Macular hole | Remove vitreous; peel internal limiting membrane (ILM); gas tamponade presses hole edges together during healing | ⚠️ Within weeks — before hole enlarges |
| Epiretinal membrane (macular pucker) | Remove vitreous; peel scar tissue layer off the macular surface to relieve distortion | Elective — when vision significantly affected |
| Vitreous haemorrhage | Clear blood from vitreous that is blocking vision; treat the underlying retinal cause (tear, new vessels) | ⚠️ Urgent if non-clearing or tractional detachment |
| Tractional retinal detachment (diabetic) | Remove vitreous and fibrovascular membranes pulling the retina off; tamponade | 🚨 Urgent — especially if macula threatened |
| Proliferative diabetic retinopathy | Clear vitreous haemorrhage; remove fibrovascular membranes; laser the retina | ⚠️ Urgent to semi-urgent depending on activity |
| Endophthalmitis (severe eye infection) | Remove infected vitreous; deliver antibiotics directly into vitreous cavity | 🚨 Emergency |
| Intraocular foreign body | Remove the vitreous to access and extract foreign material that has penetrated the eye | 🚨 Emergency |
| Dropped nucleus (cataract surgery complication) | Retrieve lens fragments that have fallen into the vitreous during cataract surgery | 🚨 Urgent |
| Dislocated IOL | Reposition or exchange an intraocular lens that has fallen or moved out of position | ⚠️ Semi-urgent |
| Severe uveitis complications | Remove opacified or inflammatory vitreous; treat severe posterior complications | Semi-urgent |
| Submacular haemorrhage (from wet AMD or PCV) | Displace blood away from the macula using gas and TPA to protect central vision | 🚨 Within 72 hours for best outcome |
25G and 27G Micro-Incision Vitrectomy — What It Means for You
The number — 25G or 27G — refers to the gauge of the instruments used. Gauge describes the diameter of the surgical port: a higher gauge means a smaller instrument. The evolution from the original 20G (0.9mm) to 23G (0.6mm) to 25G (0.5mm) and 27G (0.4mm) represents one of the most significant advances in vitreoretinal surgery over the past two decades.
| System | Port Size | Stitches? | Recovery | Best For |
|---|---|---|---|---|
| 20G (older standard) | 0.9mm | Yes — sutures required | Longer; more inflammation | Largely replaced by smaller gauge systems |
| 23G | 0.6mm | Rarely needed | Good | Complex cases requiring larger instruments |
| 25G | 0.5mm | Not needed — self-sealing | Faster; less discomfort | Most vitreoretinal cases including retinal detachment, macular surgery |
| 27G | 0.4mm | Not needed — self-sealing | Fastest recovery; least trauma | Macular surgery, selected detachments; maximum precision |
At Raahi Netradham, 25G and 27G micro-incision vitrectomy systems are available in-house. The choice between them is made by Dr. Mohit Garg or Dr. Chintan Desai based on the specific condition, complexity, and expected surgical requirements. Most macular cases are performed with 27G; most retinal detachments use 25G.
The Surgical Steps — A Plain-English Walkthrough
A quick, step-by-step guide to what happens before and during your vitrectomy procedure.
Pre-Operative Care
Complete diagnostic checks (OCT, B-scan, or biometry), informed consent, 4–6 hours fasting, and dilating eye drops prior to entering surgery.
Comfortable Anaesthesia
Performed under local anaesthesia (numbing peribulbar block) with IV sedation to keep you painless and relaxed. General anaesthesia is used when needed.
Creating Micro-Ports
Three micro-incisions are placed in the sclera for an infusion line (maintains eye pressure), a fiber-optic light pipe (illuminates retina), and surgical tools.
Vitreous Removal
A high-speed micro-cutter removes the vitreous gel while fluid continuously maintains the eye's shape, clearing direct access to the retina.
Have questions about your upcoming procedure? Consult a retinal specialist at Raahi Netradham for expert guidance and evaluation.
Retinal Surgery — The Core of the Procedure
Once the vitreous is removed, the surgeon performs the specific retinal procedure tailored to your underlying condition:
Tamponade — Filling the Eye
After retinal surgery, the vitreous cavity must be filled with something that holds the retina in position during healing. Three options are used:
| Tamponade Agent | What It Is | How Long It Stays | Face-Down Required? | When Used |
|---|---|---|---|---|
| Balanced salt solution (BSS) | Normal saline — the eye fills naturally | Permanent — absorbed and replaced by aqueous | No | Simple macular surgery without gas; selected epiretinal membrane cases |
| SF6 gas (sulphur hexafluoride) | Inert gas bubble — buoyant, pushes retina up | 2-4 weeks to absorb | Yes — duration depends on case | Macular hole (small-medium), selected retinal detachments |
| C3F8 gas (perfluoropropane) | Longer-acting inert gas | 6-8 weeks to absorb | Yes — duration depends on case | Macular hole (large), complex retinal detachments requiring longer tamponade |
| Silicone oil | Viscous silicone oil — permanent until removed | Remains until surgically removed (typically 3-6 months) | No face-down required | Complex or recurrent detachments, PVR, cases where patient cannot position |
Practical Tips for Face-Down Positioning
Following these practical adjustments makes your recovery comfortable and ensures the best surgical outcome.
Combined Phaco-Vitrectomy — When Both Operations Are Done Together
Vitrectomy accelerates cataract formation in the natural lens — approximately 70-80% of patients who have not had previous cataract surgery will develop a visually significant cataract within 1-2 years of vitrectomy. For patients over 50 who have any degree of lens clouding — even if not yet requiring cataract surgery — combined phacoemulsification cataract removal with IOL implantation plus vitrectomy (phaco-vitrectomy) is often recommended.
Single Anaesthetic
- One surgical episode rather than two separate procedures
- Reduces overall hospital visits and recovery periods
- Lower total surgical stress for the patient
Better Surgical View
- The cataract does not obscure the surgeon's view of the retina
- Allows maximum precision during micro-retinal maneuvers
- Ensures thorough peripheral vitreous removal
Faster Visual Rehabilitation
- Cataract-related blur is eliminated at the same time
- Faster return to functional everyday vision
- Avoids a secondary drop in vision due to rapid post-vitrectomy cataract growth
No Future Cataract Surgery Needed
- Permanently addresses lens clouding in a single operation
- A significant benefit for elderly or medically complex patients
- Long-term stability with artificial intraocular lens (IOL)
At Raahi Netradham, combined phaco-vitrectomy procedures are performed using advanced microsurgical systems, allowing seamless dual-specialty intervention in a single session for optimal patient comfort and clinical outcomes.
Recovery After Vitrectomy — Week by Week
Recovery after vitrectomy depends on the specific tamponade used (gas or silicone oil). Here is what to expect at each stage of your healing process:
| Timeframe | What Is Happening | What Patient Experiences | Instructions |
|---|---|---|---|
| Day 1-3 | Gas bubble large; wound healing begins | Vision very blurry (gas); mild discomfort; light sensitivity | Face-down if required; antibiotic + steroid drops; no rubbing; rest |
| Week 1 | Gas partially absorbed at edges; retina beginning to adhere | Vision clearing at edges; bubble visible as arc; mild discomfort settling | Continue drops; attend Day 1 and Week 1 follow-up; no flying |
| Weeks 2-4 | Gas continuing to absorb; retinal healing consolidating | Progressive improvement; bubble smaller; vision clearer | Drops tapering; activity gradually resuming; no flying until gas gone |
| Month 1-3 | Gas fully absorbed (if SF6); retina healing; photoreceptors recovering | Significant vision improvement; reading improving | Spectacle check at 6-8 weeks; final prescription at 3 months |
| Month 3-6 (C3F8) | Longer-acting gas absorbing; continued recovery | Further improvement; brain adapting to new vision | Continue monitoring; attend follow-up OCT |
| Silicone oil cases | Oil in place; retina held against RPE | Vision with silicone: reduced quality; colour tint | Oil removal surgery planned at 3-6 months |
Risks of Vitrectomy — Honest Information
Vitrectomy is a highly effective surgical procedure with an excellent safety profile in experienced hands. Like all intraocular surgery, it carries potential risks that should be understood before proceeding:
| Risk | Frequency | Management |
|---|---|---|
| Cataract formation | Common — 70-80% within 2 years in phakic patients | Cataract surgery planned separately or combined at the time of vitrectomy |
| Elevated intraocular pressure | Common in early post-op period (gas expansion) | Pressure-lowering drops; monitor closely; usually resolves |
| Retinal break (new tear during surgery) | Uncommon — managed with endolaser at time of surgery | Laser photocoagulation during the same procedure |
| Re-detachment | 5-10% in complex cases | Revision vitrectomy or additional procedure |
| Choroidal haemorrhage | Rare — very serious if severe | Surgical management; may affect visual outcome |
| Endophthalmitis (infection) | Very rare — <0.05% with modern technique | Intravitreal antibiotics; vitrectomy lavage |
| Ocular hypotony (low pressure) | Rare — wound leakage | Patching; suture if needed |
| Vitreous haemorrhage post-op | Uncommon | Usually absorbs; surgery if persistent |
Note: The risk-benefit balance strongly favours surgery in all the indications listed earlier in this guide. An untreated retinal detachment, macular hole, or progressive tractional detachment will result in far greater vision loss than any of the above surgical risks.
Vitrectomy at Raahi Netradham, Dehradun
| What Is Available | Detail |
|---|---|
| Surgical systems | 23G, 25G, and 27G micro-incision vitrectomy |
| Surgeons | Dr. Mohit Garg (FVRS, Sri Sankaradeva Nethralaya) | Dr. Chintan Desai (FVRSSN, Sankara Nethralaya Chennai) |
| Conditions treated | Retinal detachment | Macular hole | Epiretinal membrane | Vitreous haemorrhage | Tractional detachment | Endophthalmitis | Dropped nucleus | Dislocated IOL | Foreign body | Submacular haemorrhage |
| Tamponade options | BSS | SF6 gas | C3F8 gas | Silicone oil — all available in-house |
| Combined surgery | Phaco-vitrectomy — cataract + vitrectomy in one sitting |
| Emergency capacity | Same-day retinal detachment surgery — no waiting list for acute cases |
| Diagnostics | OCT + B-scan + fundus photography — in-house at every visit |
| NABH accreditation | Certified OT — documented sterility and safety protocols |
| Location | Haridwar Bypass Road, Ajabpur Kalan, Dehradun — 45-60 minutes from Haridwar, Rishikesh, Mussoorie |
Patients from across Uttarakhand — Haridwar, Rishikesh, Mussoorie, Tehri, Roorkee, Vikasnagar, Chakrata — do not need to travel to Delhi for vitrectomy surgery. Raahi Netradham provides the same standard of vitreoretinal surgical care as India's premier eye hospitals, without leaving the state.